
A child may only need to turn their head, move their tongue or tighten their cheeks for a clear treatment view to disappear. In paediatric dentistry, where the oral cavity is smaller and cooperation can change quickly, gaining access without crowding the mouth is an important part of planning the procedure.
A mouth gag oral expander, often described in this context as a Lip and Cheek Retractor, can help keep soft tissue away from the teeth so the clinician can see and work more clearly. The aim is not simply to open the mouth wider. It is to create controlled access while choosing a size and design that suits the child’s anatomy and the treatment being performed.
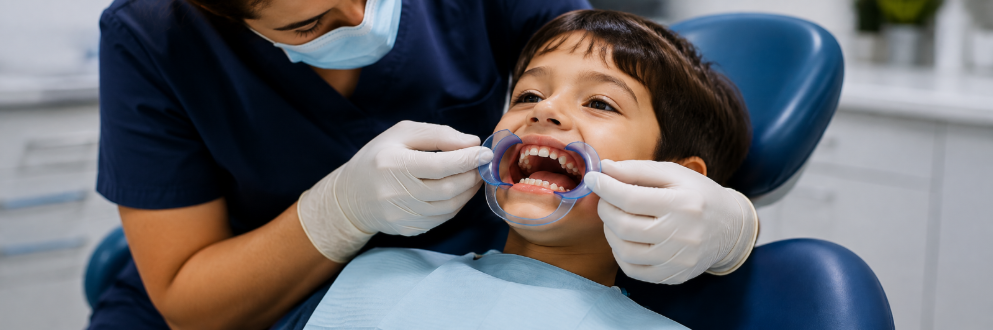
For paediatric care, the focus should remain on child-appropriate retraction rather than adapting an adult instrument to a smaller mouth. The clinician should consider oral anatomy, dentition stage, treatment site, expected procedure time and the child’s ability to tolerate the device. A well-matched retractor should create useful access without excessive stretching or unnecessary pressure. When practices are comparing child-appropriate options, Livingstone’s Range of Dental Retractors can be reviewed alongside the child’s anatomy, treatment site and tolerance.
Why is lip and cheek retraction important in paediatric dentistry?
Lip and cheek retraction is important in paediatric dentistry because it keeps mobile soft tissue away from the treatment area, improving visibility and access in a smaller oral cavity. Appropriate retraction can also reduce repeated manual repositioning while helping clinicians maintain a controlled view during treatment.
Children have less working space than adults, and the cheeks or lips can quickly obscure the tooth being examined or treated. This is especially noticeable around posterior teeth, during restorative work, or whenever the clinician needs a stable view for more than a few moments.
A suitable retractor can keep soft tissue away from rotary instruments, restorative materials, sealants and hand instruments. It does not replace careful technique, but it can make the operative field easier to manage while the clinician monitors the child’s movement and tolerance throughout the appointment. This separation may also help limit accidental soft-tissue contact with etchants, bonding agents or other materials used close to the lips and cheeks.
How does a child lip and cheek retractor improve access and visibility?
A child lip and cheek retractor improves access by holding the lips and cheeks away from the teeth without relying on continuous manual retraction. When the size and shape suit the child, the clinician gains a more consistent view of the treatment area while preserving useful space for instruments.
Manual retraction can work well for a quick examination, but longer procedures may require repeated repositioning. A dedicated retractor can provide steadier tissue displacement, which may be useful for posterior examinations, dental photography, fissure sealants and restorative procedures where the cheek repeatedly moves into the field.
The benefit depends on fit. A device that is too large can occupy valuable space or create excessive stretching, while one that is too small may slip or fail to expose the intended area. Paediatric retraction works best when the device matches both the child’s anatomy and the exact site being treated. A brief trial placement before treatment can help confirm that the selected size remains stable without crowding the working field.
What should clinicians consider when choosing a retractor for a child?
Clinicians should consider the child’s oral anatomy, the treatment site, retractor size, material, surface condition and expected procedure duration before use. A suitable paediatric retractor should expose the required area without excessive pressure, unstable positioning or unnecessary interference with other instruments in the mouth.
Age can provide a rough starting point, but it is not a reliable sizing rule on its own. Children of the same age may have different mouth sizes, dentition stages and tolerance for retraction. Mixed dentition can also change the available space around the treatment site. The clinician should assess the individual patient rather than choose a device solely from an age label.
Shape also matters. Some retractors provide broad anterior exposure, while others preserve better access to posterior teeth. A child-focused instrument selection should consider where the clinician needs visibility, how much working space is available and whether the design can remain stable without interfering with instruments or suction.
When is a mouth gag oral expander useful during paediatric treatment?
A mouth gag oral expander can be useful when paediatric treatment requires sustained soft-tissue retraction, clearer visual access or a more stable working field. It may be considered for restorative procedures, sealants, photography and selected examinations, provided the child tolerates the device and the size is appropriate.
Not every appointment needs a retractor. A short visual examination may only require gentle manual retraction, while a longer procedure may benefit from a device that keeps the lips and cheeks consistently away from the tooth. This can be particularly useful when the clinician needs both hands available for instrumentation. The clinical task should determine whether the instrument adds value.
Children who are anxious, very young or unable to tolerate the device should not be forced to continue with it simply to maintain access. Positioning should be reassessed if the child shows discomfort, tissue blanching, distress or repeated attempts to dislodge the retractor. Behaviour guidance and clinical judgement remain central to paediatric care.
How should retractor size be selected for a child?
Retractor size for a child should be selected according to individual oral anatomy, dentition stage, treatment site and tolerance rather than age alone. The device should provide stable soft-tissue displacement without excessive stretching, crowding the mouth or reducing the working space needed for instruments and suction.
A quick visual assessment before placement can help determine whether the chosen retractor is proportionate to the child’s mouth. The clinician should consider lip width, cheek flexibility, tooth position and whether the child is in primary, mixed or permanent dentition. These factors can change the amount and direction of retraction required.
Fit should be reassessed once the retractor is in place. If it slips, presses heavily on the commissures, creates blanching or occupies too much of the working field, another size or design may be more appropriate. Keeping more than one paediatric option available allows the instrument to be matched to the patient rather than forcing one size to suit every child.
How should reusable paediatric retractors be cleaned and reprocessed?
Reusable paediatric retractors should be cleaned and reprocessed after each patient according to the manufacturer’s instructions and the dental practice’s validated infection-prevention procedures. Staff should confirm whether cleaning, disinfection or sterilisation is required for the specific device and inspect it for damage before storage or reuse.
A retractor that contacts the oral cavity enters the practice’s established instrument-management workflow after use. Cleaning should remove visible soil before any required disinfection or sterilisation step, and the device should be dry, intact and appropriately stored before it returns to clinical use. Staff should also check for cracks, warping or roughened surfaces that could affect safe placement or make cleaning more difficult.
Reprocessing requirements can vary between paediatric retractors because materials and manufacturer instructions differ. Staff should therefore confirm the validated cleaning and sterilisation method for the exact device in use rather than assuming that every reusable retractor can be processed in the same way.
How can paediatric dental teams choose the right retractor for routine care?
Paediatric dental teams can choose the right retractor by matching the instrument to the child’s anatomy, treatment site, procedure duration and tolerance rather than relying on one universal size. Keeping child-appropriate options available allows retraction to be adjusted to the patient instead of making the patient adapt to the instrument.
The most useful retractor is the one that creates enough access without introducing unnecessary pressure or taking up more space than the procedure requires. A quick check of fit, surface condition and positioning before treatment can prevent avoidable interruptions once the procedure begins. For practices that regularly treat children, maintaining more than one paediatric size or design can make this patient-specific approach easier to apply consistently. Practices that buy mouth gags online should compare paediatric sizing, intended use, material and reprocessing instructions. They can also review a broader range of dental retractors before ordering, rather than relying on a generic product label.
For paediatric dentistry, effective retraction comes from choosing a child lip and cheek retractor or another suitably sized design that fits the individual patient and procedure. The practical takeaway is simple: choose for the child first, confirm comfortable and stable positioning, and make sure the instrument can be safely reprocessed before reuse.
References
Australian Commission on Safety and Quality in Health Care 2024, Advisory PCHS24/01: National Safety and Quality Primary and Community Healthcare Standards requirements for reprocessing of reusable medical devices in practices, viewed 26 August 2026.
Australian Commission on Safety and Quality in Health Care 2024, Transitioning from AS/NZS 4815:2006 to AS 5369:2023, viewed 26 August 2026.
Australian Dental Association 2022, Guidelines for Infection Prevention and Control, Fifth Amended Edition, viewed 26 August 2026.







